


When people stop Zepbound (tirzepatide) or Wegovy (semaglutide), most regain a large share of the lost weight within a year, and appetite returns as the drug clears over about four to seven weeks. Gains in blood pressure, blood sugar and cholesterol also drift back. A minority keep most of the loss, and lower-dose and oral maintenance options are being tested.
That is the short answer to “what happens when you stop Zepbound”, and to the near-identical questions about Wegovy and Ozempic. It is also the question filling weight-loss forums this autumn, as people reach their goal weight, worry about losing employer coverage in 2027, or simply do not want to take an injection for life.
This guide sets out what the randomised withdrawal trials found, how quickly appetite and weight come back, what the newer maintenance studies show, and the legal lower-cost routes if coverage ends. It is part of our research peptides and GLP-1 coverage. It does not give dosing or tapering schedules: any change should be planned with the prescriber.
At a glance
| Question | What the evidence shows |
|---|---|
| Weight a year after stopping semaglutide | About two-thirds of the lost weight regained (STEP 1 extension)1 |
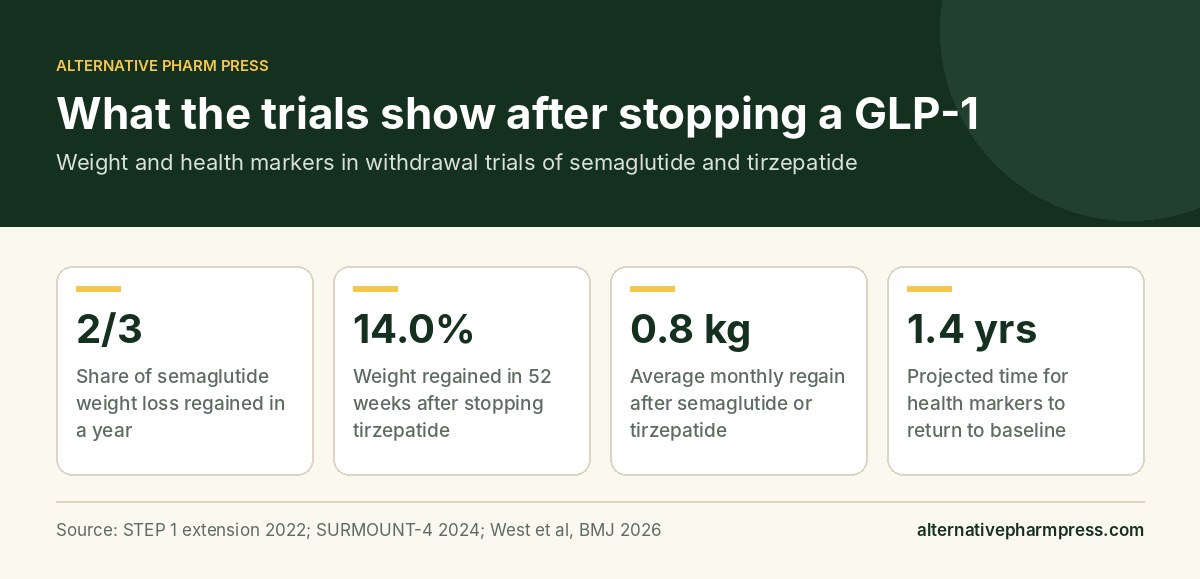
| Weight after stopping tirzepatide | 14.0% regained over 52 weeks on placebo, while those who continued lost a further 5.5% (SURMOUNT-4)3 |
| Average rate of regain | About 0.8 kg a month after semaglutide or tirzepatide, in a 2026 meta-analysis5,6 |
| Blood pressure, glucose, lipids | Drift back towards baseline; projected to get there within about 1.4 years5 |
| When the drug leaves the body | Semaglutide 5 to 7 weeks; tirzepatide about 30 days8,9 |
| Lower-dose maintenance | Tirzepatide 5 mg kept more weight off than placebo but less than the full dose11 |
| Switching to a pill | Orforglipron kept 75% to 79% of prior loss, against 38% to 49% on placebo12 |
What happens when you stop Zepbound or Wegovy: why weight comes back
Semaglutide and tirzepatide mimic gut hormones that signal fullness. Tirzepatide acts on both GLP-1 and GIP receptors; semaglutide acts on GLP-1 alone (our guide to glucagon-like peptides explains the receptor family). In a 20-week study of 72 adults, semaglutide 2.4 mg cut the amount people ate at a free-choice lunch by 35% compared with placebo, reduced hunger and led to fewer and weaker food cravings.10
Those effects last only while the drug is present. The medicines do not reset appetite permanently, and the body’s drive to regain lost weight remains. That is why the trial authors, and most obesity specialists, describe obesity as a chronic condition that usually needs ongoing treatment. For how the two drugs compare while you are on them, see semaglutide vs tirzepatide.
Stopping Wegovy: the STEP 1 extension and STEP 4
STEP 1 extension. In the main STEP 1 trial, people took semaglutide 2.4 mg or placebo for 68 weeks, then stopped both the drug and the lifestyle programme. A subset of 327 participants was followed for another year. The semaglutide group had lost 17.3% of body weight by week 68. By week 120 they had regained 11.6 percentage points, leaving a net loss of 5.6%, compared with 0.1% in the placebo group. Put simply, they regained about two-thirds of what they had lost. Most cardiometabolic improvements also reverted towards baseline.1 The extension was exploratory, and the lifestyle support ended at the same time as the drug.
STEP 4. This randomised trial in JAMA tested withdrawal directly. After a 20-week run-in on semaglutide, during which people lost an average of 10.6%, 803 participants were randomised to keep taking it or switch to placebo for 48 weeks. Those who continued lost a further 7.9%; those switched to placebo regained 6.9%. Waist size and systolic blood pressure were also better with continued treatment.2
Stopping Zepbound: what SURMOUNT-4 found
SURMOUNT-4 gave 783 adults tirzepatide at their maximum tolerated dose for 36 weeks. The 670 who completed this phase had lost an average of 20.9%. They were then randomised to continue or switch to placebo for 52 weeks. The placebo group regained 14.0% of body weight, while the tirzepatide group lost a further 5.5%. At week 88, 89.5% of those still on tirzepatide had kept at least 80% of their earlier weight loss, compared with 16.6% on placebo.3
One detail is often missed: over the full 88 weeks, the placebo group was still 9.9% lighter than at the start. Stopping did not erase all of the benefit within a year, but the trend was clearly upward.
A 2026 post hoc analysis of 308 people who stopped tirzepatide looked at how much each person regained. Only 54 (about 18%) regained less than a quarter of their lost weight; 74 regained three-quarters or more. The more people regained, the more their health markers rebounded: in the group that regained the most, waist size rose by 14.7 cm and systolic blood pressure by 10.4 mm Hg. Even those who regained the least saw systolic blood pressure rise by 6.8 mm Hg.4
Stopping Ozempic and other GLP-1s: what the pooled studies show
A systematic review in The BMJ in January 2026 pooled 37 studies with 9,341 participants who stopped weight-management medicines. Across all drugs, weight came back at an average of 0.4 kg a month, faster than after stopping diet and behaviour programmes, and cardiometabolic markers were projected to return to baseline within 1.4 years.5 For semaglutide and tirzepatide specifically, the authors reported regain of about 0.8 kg a month, with a projected return to starting weight in around 1.5 years, although data beyond 12 months are limited.6
A second meta-analysis of 18 randomised trials (3,771 participants) found that people with obesity regained an average of 5.63 kg after stopping a GLP-1 drug, with HbA1c rising by 0.25 percentage points. In people with type 2 diabetes, HbA1c rose by 0.65 points.7 That matters for anyone searching “stopping Ozempic”: Ozempic is semaglutide licensed for diabetes, and stopping it can affect blood sugar control, not just weight. Any change to diabetes treatment needs a plan from the prescriber.
Appetite and “food noise”: how quickly do they come back?
The drugs do not vanish the day after the last dose. According to the Wegovy label, semaglutide has an elimination half-life of about one week and stays in the circulation for about 5 to 7 weeks after the last dose.8 Lilly states that tirzepatide has a half-life of about 5 days and should be gone from the body in about 30 days.9 So appetite suppression fades over weeks rather than overnight.
No trial we found tracked appetite week by week after stopping. Forum reports of hunger and cravings returning within a month or two fit the pharmacology, but they are anecdotal. In a 2026 qualitative study of 30 US patients, a reduction in “food noise” was one of the most valued effects, and participants described the drugs as a support for lifestyle change rather than a replacement for it.21
Another common worry is that the drug works less well on a second course. We found no randomised trial that tested this directly, so the honest answer is that it is unknown. Restarting after a break is still a conversation for the prescriber, because gastrointestinal side effects are most common during dose escalation.11
Is there a better way to come off? Maintenance and dose-reduction research
The most useful new evidence published in 2026 tests stepping down rather than stopping outright. These are trial designs, not instructions.
SURMOUNT-MAINTAIN (The Lancet, 2026). After 60 weeks on full-dose tirzepatide, 378 adults were randomised to stay on their maximum tolerated dose, drop to 5 mg, or switch to placebo for 52 weeks. Total weight change from the start was 21.9% with the full dose, 16.6% with 5 mg and 9.9% with placebo. Rescue treatment for regaining at least half of the lost weight was needed by 8%, 25% and 67% of each group respectively. The authors say dose reduction “might provide a valuable alternative to discontinuation”, while noting that individual responses vary.11 The trial was funded by Lilly.
ATTAIN-MAINTAIN (Nature Medicine, 2026). People who had taken Zepbound or Wegovy for 72 weeks in another trial were switched to Lilly’s daily pill orforglipron (Foundayo) or placebo for a year. The tirzepatide group kept 74.7% of their weight loss on orforglipron against 49.2% on placebo; the semaglutide group kept 79.3% against 37.6%. There was no arm that simply continued the injections, and follow-up lasted one year.12 Our Foundayo vs Wegovy pill comparison covers both tablets.
Gradual tapering. Some clinics stretch the interval between doses or step down slowly. So far, the published evidence for this is limited to small case series. We found no randomised trial showing that tapering to zero prevents regain.
Exercise. The best evidence comes from an older daily GLP-1, liraglutide (see semaglutide vs liraglutide). In a Danish trial, adults first lost 13.1 kg on a low-calorie diet, then spent a year on liraglutide, supervised exercise, both, or placebo. One year after all treatment stopped, regain after liraglutide alone was 6.0 kg larger than after exercise alone, and the combination group was 5.1 kg lighter than the liraglutide-only group.13 Only 109 participants attended the follow-up, but it is the clearest signal that building an exercise habit while on the drug helps afterwards.
Why people are stopping: the 2027 coverage changes
Many people are not choosing to stop. In June 2026, Reuters reported that 10% of employers that cover GLP-1s for weight loss plan to drop them in 2027, according to the Business Group on Health, and that 5% of large employers plan to do so, according to Mercer. Mercer found that 44% of large employers currently cover these drugs. Cigna stopped covering weight-loss drugs for its own employees from July.14
Medicare is moving the other way. The Medicare GLP-1 Bridge, which began on 1 July 2026, offers Wegovy and Zepbound to eligible Part D enrollees for $50 a prescription; eligibility requires a BMI of 35 or more, or 27 or more with other clinical criteria.15,16 CMS says the Bridge has been extended to 31 December 2027.16
If an employer plan is dropping obesity coverage, ask the prescriber and insurer whether another approved indication applies. Wegovy is also approved to reduce cardiovascular risk in adults with established heart disease and for a form of fatty liver disease (MASH),8 and Zepbound is approved for moderate to severe obstructive sleep apnoea in adults with obesity.22 Coverage for those uses depends on each plan’s rules.
Legal lower-cost options if you pay yourself
Both manufacturers now sell direct to self-paying patients with a prescription. Prices below were checked in October 2026 and change often.
| Option | Self-pay price | Notes |
|---|---|---|
| Zepbound vials or KwikPen (LillyDirect) | $299 to $449 a month | Higher doses cost up to $699 unless refilled within 45 days17 |
| Wegovy pen (NovoCare) | $349 a month | $199 for the first two fills for new patients, to 31 Dec 202618 |
| Wegovy pill (NovoCare) | $149 to $299 a month | Price depends on dose18 |
| Foundayo (orforglipron) | About $149 to $299 a month | Through LillyDirect or select telehealth services19 |
| Medicare GLP-1 Bridge | $50 a prescription | Eligible Part D enrollees only15,16 |
Self-pay costs do not count towards insurance deductibles.18 This is not financial advice; compare the total yearly cost with your clinician and insurer before deciding.
Grey-market and “research” GLP-1s: what the FDA warns
When costs rise, some people look at semaglutide, tirzepatide or retatrutide sold online as “research chemicals”. The FDA has warned companies selling these products labelled “for research purposes” or “not for human consumption” that were in fact marketed for human use. The agency says their quality is unknown and that consumers should not buy them. It has also flagged counterfeit Ozempic and semaglutide salt forms that differ from the approved drug.20
As of 31 May 2026, the FDA had received 990 adverse event reports for compounded semaglutide and more than 730 for compounded tirzepatide, including hospitalisations linked to dosing errors, and it believes the true number is higher because many pharmacies are not required to report.23 Retatrutide is not approved at all; see retatrutide vs tirzepatide for its trial status. Our explainers on what “research use only” means and weight-loss peptides in 2026 cover the legal landscape in more detail.
Planning to stop: questions to take to your prescriber
- Why am I stopping? Cost, side effects, reaching a goal or planning a pregnancy each point to different options. If contraception or pregnancy is part of the picture, our guide to Zepbound and birth control explains why tirzepatide matters for the pill.
- Is a lower maintenance dose or an oral switch suitable for me? Both have trial data from 2026, but neither suits everyone.
- What should we monitor afterwards? Weight, waist, blood pressure, HbA1c and lipids, with a date for the first check.
- Do any other medicines need adjusting? This is essential for anyone with type 2 diabetes.
- What support is available? A dietitian, a structured exercise programme or a behavioural weight-management service.
- At what point would we consider restarting? Agreeing a threshold in advance makes the decision easier later.
Frequently asked questions
How fast do you regain weight after stopping Zepbound?
In SURMOUNT-4, people switched from tirzepatide to placebo regained 14.0% of body weight over 52 weeks, and only 16.6% kept at least 80% of their earlier loss. A 2026 meta-analysis put the average regain after semaglutide or tirzepatide at about 0.8 kg a month. Individual results vary widely, and some people regain much less.
Does appetite come back after stopping Wegovy?
Usually, yes. Semaglutide reduces hunger and cravings while it is in the body, and the Wegovy label says it remains in circulation for about 5 to 7 weeks after the last dose. No trial has tracked appetite week by week after stopping, but the steady regain seen in withdrawal trials suggests appetite returns towards its previous level.
Can you taper off a GLP-1 to avoid regaining weight?
There is no proven taper to zero. The strongest evidence is for stepping down rather than stopping: in SURMOUNT-MAINTAIN, a lower tirzepatide dose kept more weight off than placebo, and in ATTAIN-MAINTAIN switching to the orforglipron pill helped too. Slow tapering schedules have only small case series behind them, so plan any change with your prescriber.
Is stopping Ozempic different if you have type 2 diabetes?
It can be. Ozempic is semaglutide licensed for diabetes, and a 2025 meta-analysis found HbA1c rose by about 0.65 percentage points after people with type 2 diabetes stopped a GLP-1 drug. Blood sugar control, not just weight, needs a plan. Never stop or swap diabetes medicines without speaking to the clinician who manages your diabetes.
Are research-grade semaglutide or tirzepatide a safe cheaper option?
No. The FDA has warned companies selling semaglutide, tirzepatide and retatrutide labelled for research or not for human consumption, and says the quality of these products is unknown. Legal lower-cost routes include manufacturer self-pay programmes, the Wegovy pill and Foundayo, and Medicare’s GLP-1 Bridge for eligible Part D enrollees.
Sources
- Wilding JPH, Batterham RL, Davies M, et al; STEP 1 Study Group. Weight regain and cardiometabolic effects after withdrawal of semaglutide: the STEP 1 trial extension. Diabetes Obes Metab. 2022;24(8):1553-1564. PMID: 35441470. pubmed.ncbi.nlm.nih.gov
- Rubino D, Abrahamsson N, Davies M, et al; STEP 4 Investigators. Effect of continued weekly subcutaneous semaglutide vs placebo on weight loss maintenance in adults with overweight or obesity: the STEP 4 randomized clinical trial. JAMA. 2021;325(14):1414-1425. PMID: 33755728. pubmed.ncbi.nlm.nih.gov
- Aronne LJ, Sattar N, Horn DB, et al; SURMOUNT-4 Investigators. Continued treatment with tirzepatide for maintenance of weight reduction in adults with obesity: the SURMOUNT-4 randomized clinical trial. JAMA. 2024;331(1):38-48. PMID: 38078870. pubmed.ncbi.nlm.nih.gov
- Horn DB, Linetzky B, Davies MJ, et al. Cardiometabolic parameter change by weight regain on tirzepatide withdrawal in adults with obesity: a post hoc analysis of the SURMOUNT-4 trial. JAMA Intern Med. 2026;186(2):157-167. PMID: 41284285. pubmed.ncbi.nlm.nih.gov
- West S, Scragg J, Aveyard P, et al. Weight regain after cessation of medication for weight management: systematic review and meta-analysis. BMJ. 2026;392:e085304. PMID: 41500720. pubmed.ncbi.nlm.nih.gov
- University of Oxford, Medical Sciences Division. Stopping weight-loss drugs linked to faster regain than ending diet programmes, finds new review. January 2026. medsci.ox.ac.uk
- Tzang CC, Wu PH, Luo CA, et al. Metabolic rebound after GLP-1 receptor agonist discontinuation: a systematic review and meta-analysis. EClinicalMedicine. 2025;90:103680. PMID: 41399474. pubmed.ncbi.nlm.nih.gov
- Novo Nordisk. WEGOVY (semaglutide) injection and tablets: US prescribing information. novo-pi.com
- Lilly Medical. How long will Zepbound (tirzepatide) be in the body after the last dose? Last reviewed 19 December 2024. medical.lilly.com
- Friedrichsen M, Breitschaft A, Tadayon S, Wizert A, Skovgaard D. The effect of semaglutide 2.4 mg once weekly on energy intake, appetite, control of eating, and gastric emptying in adults with obesity. Diabetes Obes Metab. 2021;23(3):754-762. PMID: 33269530. pubmed.ncbi.nlm.nih.gov
- Horn DB, Aronne LJ, Wharton S, et al. Tirzepatide for maintenance of bodyweight reduction in people with obesity in the USA (SURMOUNT-MAINTAIN): a multicentre, double-blind, randomised, placebo-controlled trial. Lancet. 2026;407(10545):2305-2318. PMID: 42119587. pubmed.ncbi.nlm.nih.gov
- Aronne LJ, Horn DB, le Roux CW, et al. Orforglipron for maintenance of body weight reduction: the double-blind, randomized phase 3b ATTAIN-MAINTAIN trial. Nat Med. 2026;32(7):2679-2687. PMID: 42120723. pubmed.ncbi.nlm.nih.gov
- Jensen SBK, Blond MB, Sandsdal RM, et al. Healthy weight loss maintenance with exercise, GLP-1 receptor agonist, or both combined followed by one year without treatment: a post-treatment analysis of a randomised placebo-controlled trial. EClinicalMedicine. 2024;69:102475. PMID: 38544798. pubmed.ncbi.nlm.nih.gov
- Niasse A. Some US employers to drop coverage of GLP-1 obesity drugs in 2027 as use increases. Reuters, via MarketScreener. 11 June 2026. marketscreener.com
- Cubanski J. What Medicare’s temporary program covering GLP-1s for obesity means for beneficiaries. KFF. 9 March 2026. kff.org
- Centers for Medicare & Medicaid Services. BALANCE Model and Medicare GLP-1 Bridge. Last modified 29 September 2026. cms.gov
- Eli Lilly and Company. LillyDirect: Zepbound self-pay pricing. Accessed October 2026. lilly.com
- Novo Nordisk. NovoCare: price your Wegovy. Accessed October 2026. novocare.com
- Ro. Foundayo cost: self-pay pricing. Updated 31 August 2026. ro.co
- US Food and Drug Administration. FDA’s concerns with unapproved GLP-1 drugs used for weight loss. fda.gov
- de Vere Hunt I, Ramirez-Posada M, Babu CS, et al. Patient experiences with GLP-1 receptor agonists. JAMA Netw Open. 2026;9(6):e2616951. PMID: 42247231. pubmed.ncbi.nlm.nih.gov
- Healio. FDA approves Zepbound for moderate to severe OSA in adults with obesity. 20 December 2024. healio.com
- Becker’s Hospital Review. FDA warns clinicians on compounded GLP-1s amid 1,700+ safety reports. 8 September 2026. beckershospitalreview.com
Featured image: The 'magic' Bathroom Scale by mark6mauno, CC BY 2.0. Cropped.
This article is for educational purposes only and is not medical or legal advice. Products discussed here are not intended to diagnose, treat, cure or prevent any disease. Laws vary by location and change often, so verify the rules that apply where you are. Always talk to a licensed healthcare provider before use, especially if you are under 21, pregnant or nursing, taking medication, or managing a health condition.